How Hemochromatosis Triggers Headaches and Other Warning Signs
What Is Hemochromatosis and Why It Matters
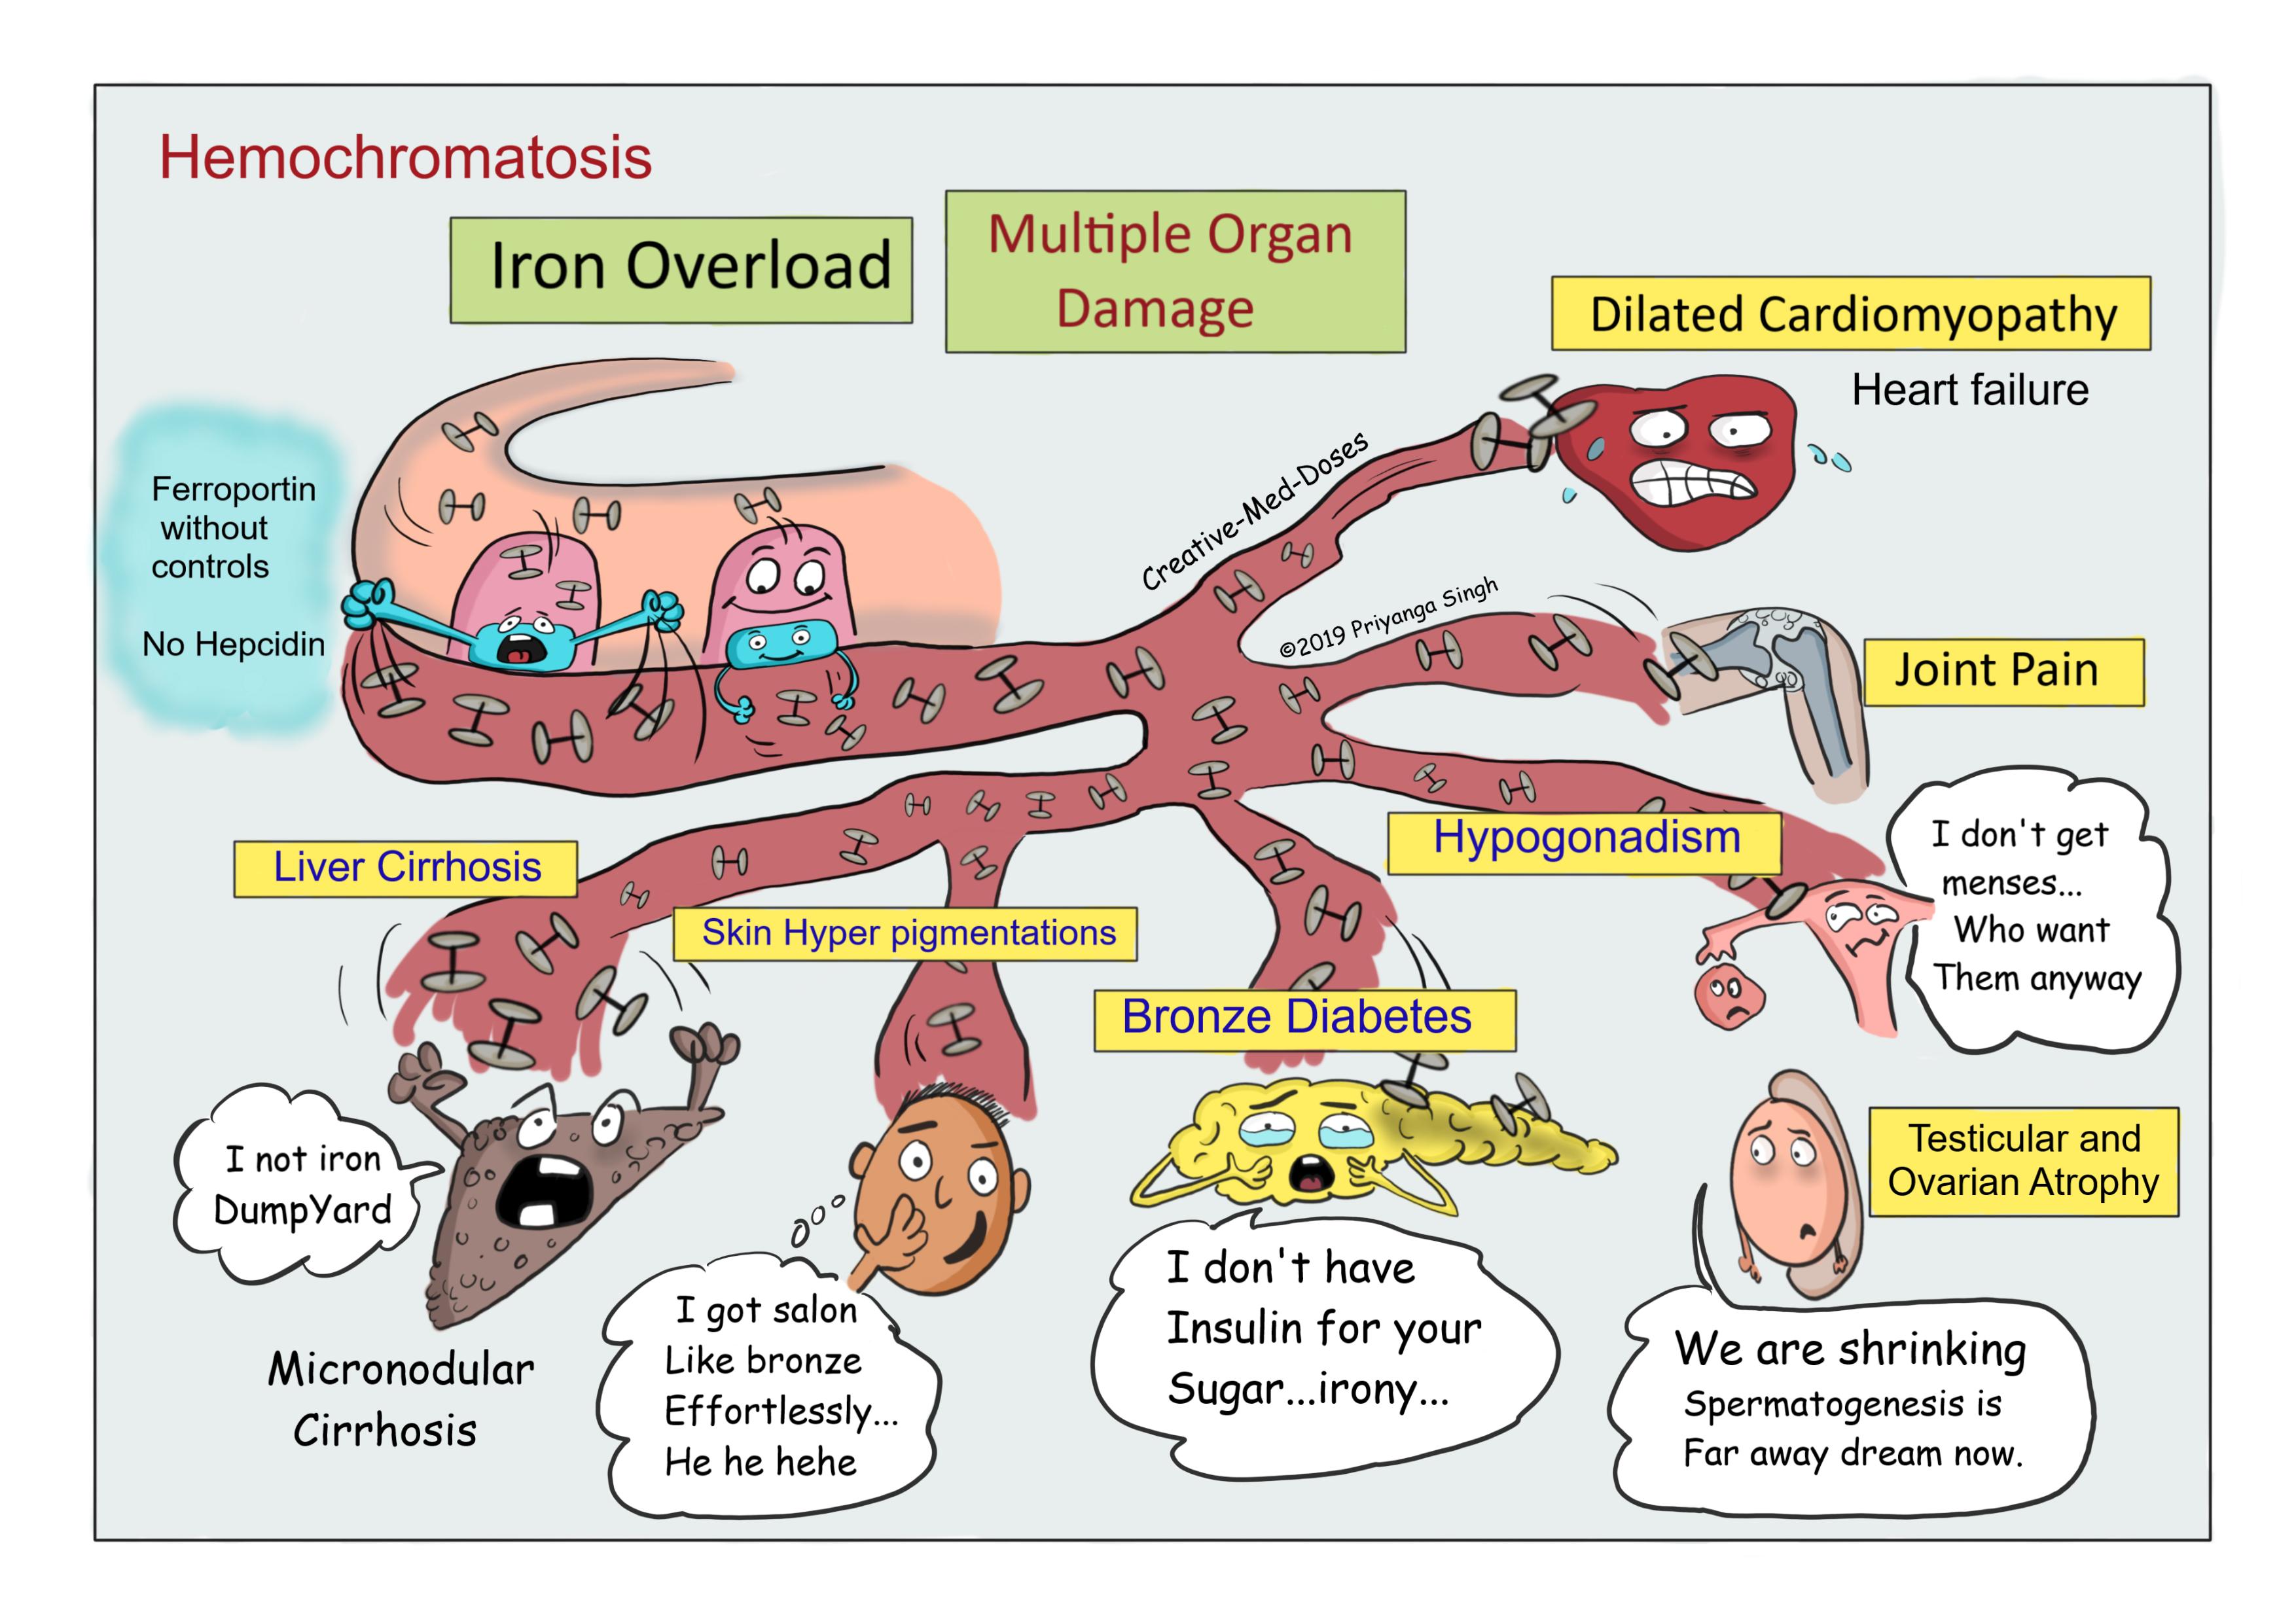
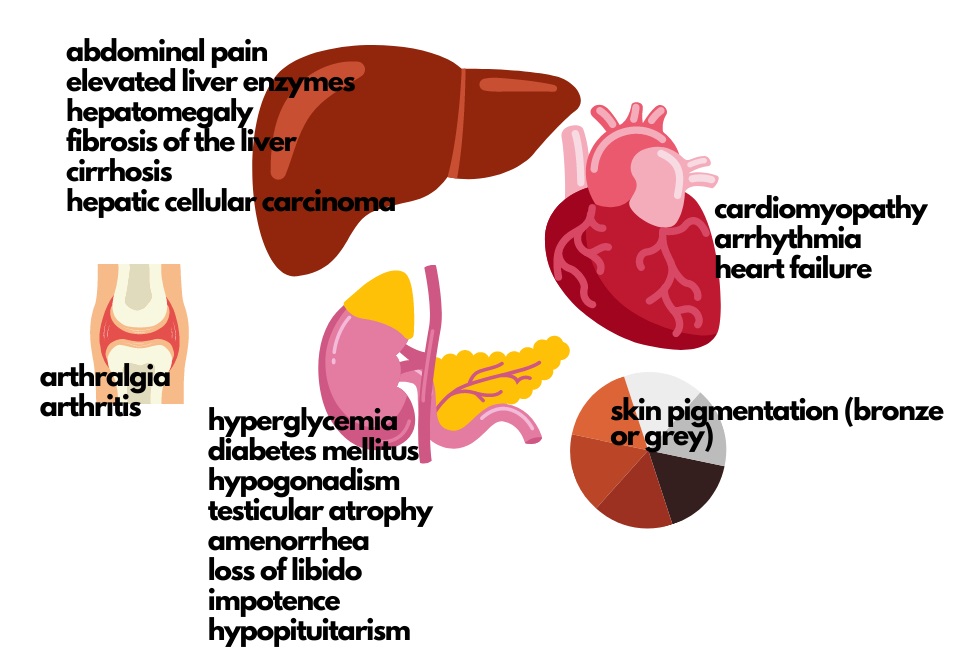
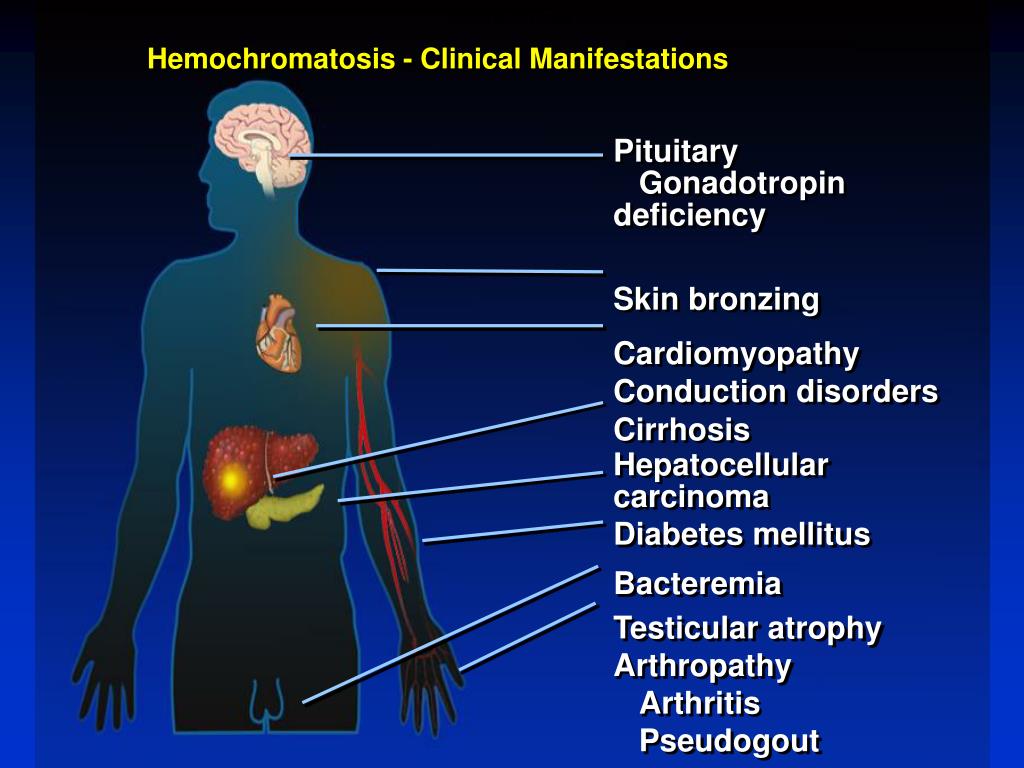
Hemochromatosis is a genetic condition that makes the body absorb too much iron from food. Over time, that excess iron builds up in organs such as the liver, heart, pancreas, and even the brain. When iron starts to accumulate where it shouldn’t, a range of symptoms can surface—some obvious, others surprisingly subtle.
Most people associate hemochromatosis with fatigue or joint pain, but headaches are a surprisingly common complaint. Understanding why a simple ache can be a red flag helps catch the disease early, before irreversible damage occurs.
Why Headaches Occur in Hemochromatosis
The link between iron overload and headaches isn’t straightforward, yet a few mechanisms make sense.
- Iron deposition in brain tissue. Excess iron can settle in the basal ganglia and other regions that regulate blood flow, leading to intermittent pressure changes.
- Oxidative stress. Too much iron fuels free‑radical formation, which irritates blood vessels and can provoke migraine‑like throbbing.
- Hormonal imbalances. The condition often disrupts thyroid function; an underactive thyroid is a known headache trigger.
Because each of these factors can act alone or together, the headache pattern varies. Some people describe a dull, persistent ache, while others get sudden, sharp pains that mimic classic migraines.
Other Common Symptoms to Watch For
Headaches rarely appear in isolation. If you notice any of the following alongside them, it’s worth discussing iron studies with your doctor.
- Joint pain, especially in the knuckles. The second and third metacarpophalangeal joints often feel stiff or swollen.
- Skin discoloration. A bronze or gray hue can develop, most noticeable on the face and hands.
- Fatigue that doesn’t improve with rest. Iron overload paradoxically makes you feel exhausted rather than energized.
- Abdominal discomfort. An enlarged liver or spleen may cause a vague, lingering ache.
- Changes in heart rhythm. Palpitations or a feeling of “fluttering” can signal cardiac iron deposition.
These signs can be subtle for years, which is why many patients are diagnosed only after a routine blood test flags high ferritin levels.
How Doctors Diagnose Iron‑Related Headaches
When you bring up frequent headaches, a clinician will typically start with a thorough medical history. If they suspect hemochromatosis, they’ll order a series of blood tests:
- Serum ferritin. Elevated ferritin often hints at excess iron storage.
- Transferrin saturation. Values above 45 % are a strong red flag.
- Genetic testing. The HFE gene mutation (C282Y and H63D) confirms hereditary hemochromatosis in most cases.
Imaging isn’t always required, but an MRI can reveal iron deposits in the liver or brain, helping explain persistent headaches when blood work alone is inconclusive.
Managing Headaches and Reducing Iron Load
Treatment focuses on two fronts: lowering the body’s iron stores and addressing the headache itself.
Therapeutic Phlebotomy
Regular blood removal—often called therapeutic phlebotomy—is the gold‑standard approach. Each session extracts about 500 ml of blood, which forces the body to use stored iron to make new red blood cells. Most patients notice a reduction in headache frequency after a few months of consistent treatment.
Dietary Adjustments
While phlebotomy does the heavy lifting, diet can support the process. Consider these practical steps:
- Limit red meat, especially organ meats, which are iron‑dense.
- Avoid vitamin C supplements taken with meals, as vitamin C boosts iron absorption.
- Enjoy tea or coffee with meals; polyphenols in these drinks bind iron and reduce uptake.
Headache‑Specific Relief
Standard migraine or tension‑type headache remedies still apply. Over‑the‑counter NSAIDs can help, but talk to your doctor first—some can strain the liver, which may already be compromised.
In more chronic cases, a neurologist might suggest preventive medications such as beta‑blockers or calcium channel blockers, chosen to avoid interfering with iron metabolism.
Living With Hemochromatosis: Lifestyle Tips
Beyond medical treatment, everyday habits make a difference.
- Regular monitoring. Schedule ferritin checks every six months after you reach target levels.
- Stay active. Moderate exercise supports cardiovascular health, which can offset iron‑related heart strain.
- Limit alcohol. Alcohol adds stress to the liver, a key organ already at risk from iron overload.
- Educate your family. Since the condition is hereditary, relatives may benefit from early screening.
Adopting these practices doesn’t cure hemochromatosis, but it can keep the disease well‑controlled and reduce the chance that headaches become a chronic nuisance.
Frequently Asked Questions
Can a single blood test diagnose hemochromatosis?
A single ferritin measurement can suggest iron overload, but definitive diagnosis usually requires both transferrin saturation and genetic testing.
Do all people with hemochromatosis get headaches?
No. Headaches are common but not universal; many patients first notice joint pain or skin changes before any cranial symptoms appear.
Is therapeutic phlebotomy safe for older adults?
Yes, when performed under medical supervision. The frequency may be adjusted based on overall health, anemia risk, and how quickly ferritin levels drop.
Can lifestyle changes alone normalize iron levels?
Diet and avoiding excess vitamin C can modestly reduce absorption, but they rarely bring ferritin into the normal range without phlebotomy.