What the Latest IGLP‑1 Diabetes Guidelines Mean for Patients
When the IGLP 1 Diabetes Guidelines Explained hit the medical community, clinicians and patients alike scrambled to understand what really changed. In plain language, these recommendations refine how we think about GLP‑1‑based therapies for type 2 diabetes, emphasizing individualized care, cardiovascular safety, and practical prescribing tips. Below, we break down the most relevant updates and translate them into everyday decisions.
Key Changes in the IGLP‑1 Diabetes Guidelines
The new guidance pivots on three central themes: risk‑based patient selection, broader outcome metrics, and a more flexible sequencing of injectable agents. Here’s what that looks like in practice.
- Risk stratification becomes front‑and‑center. Rather than a one‑size‑fits‑all approach, the guidelines urge clinicians to assess cardiovascular disease (CVD) risk, renal function, and obesity severity before choosing a GLP‑1 receptor agonist.
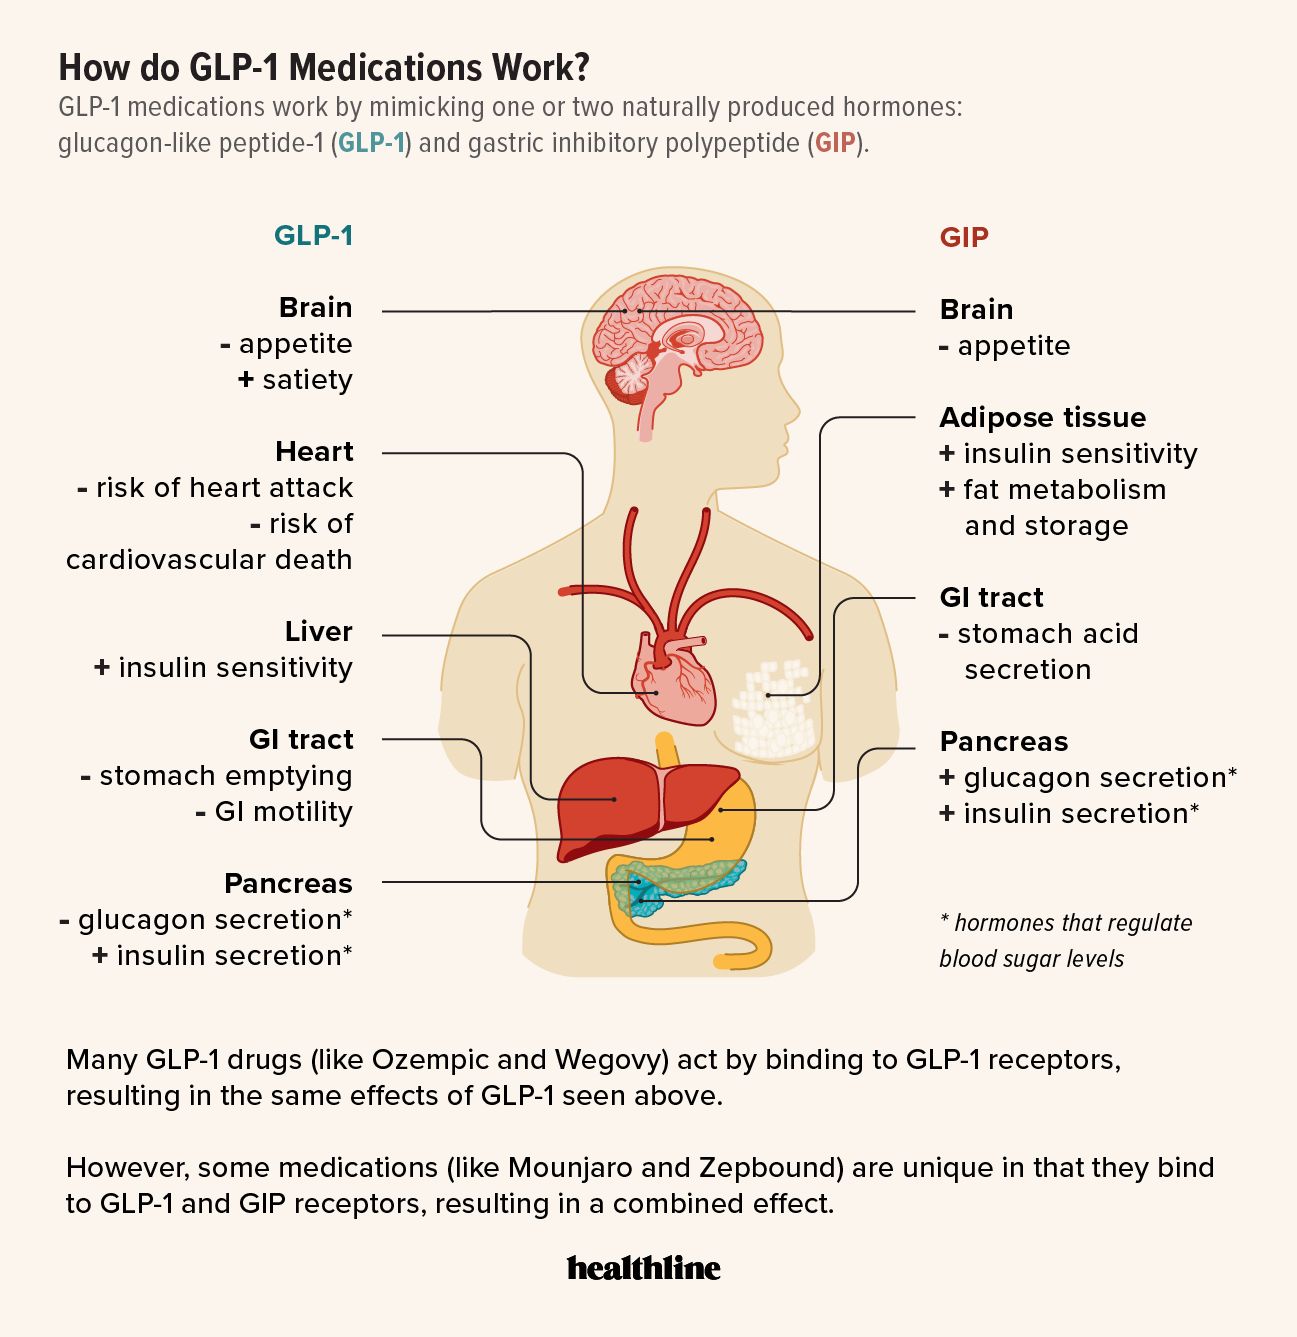
- Cardiovascular benefit is now a primary endpoint. Trials that demonstrated reduced major adverse cardiovascular events (MACE) are highlighted, nudging prescribers toward agents with proven heart protection for high‑risk patients.
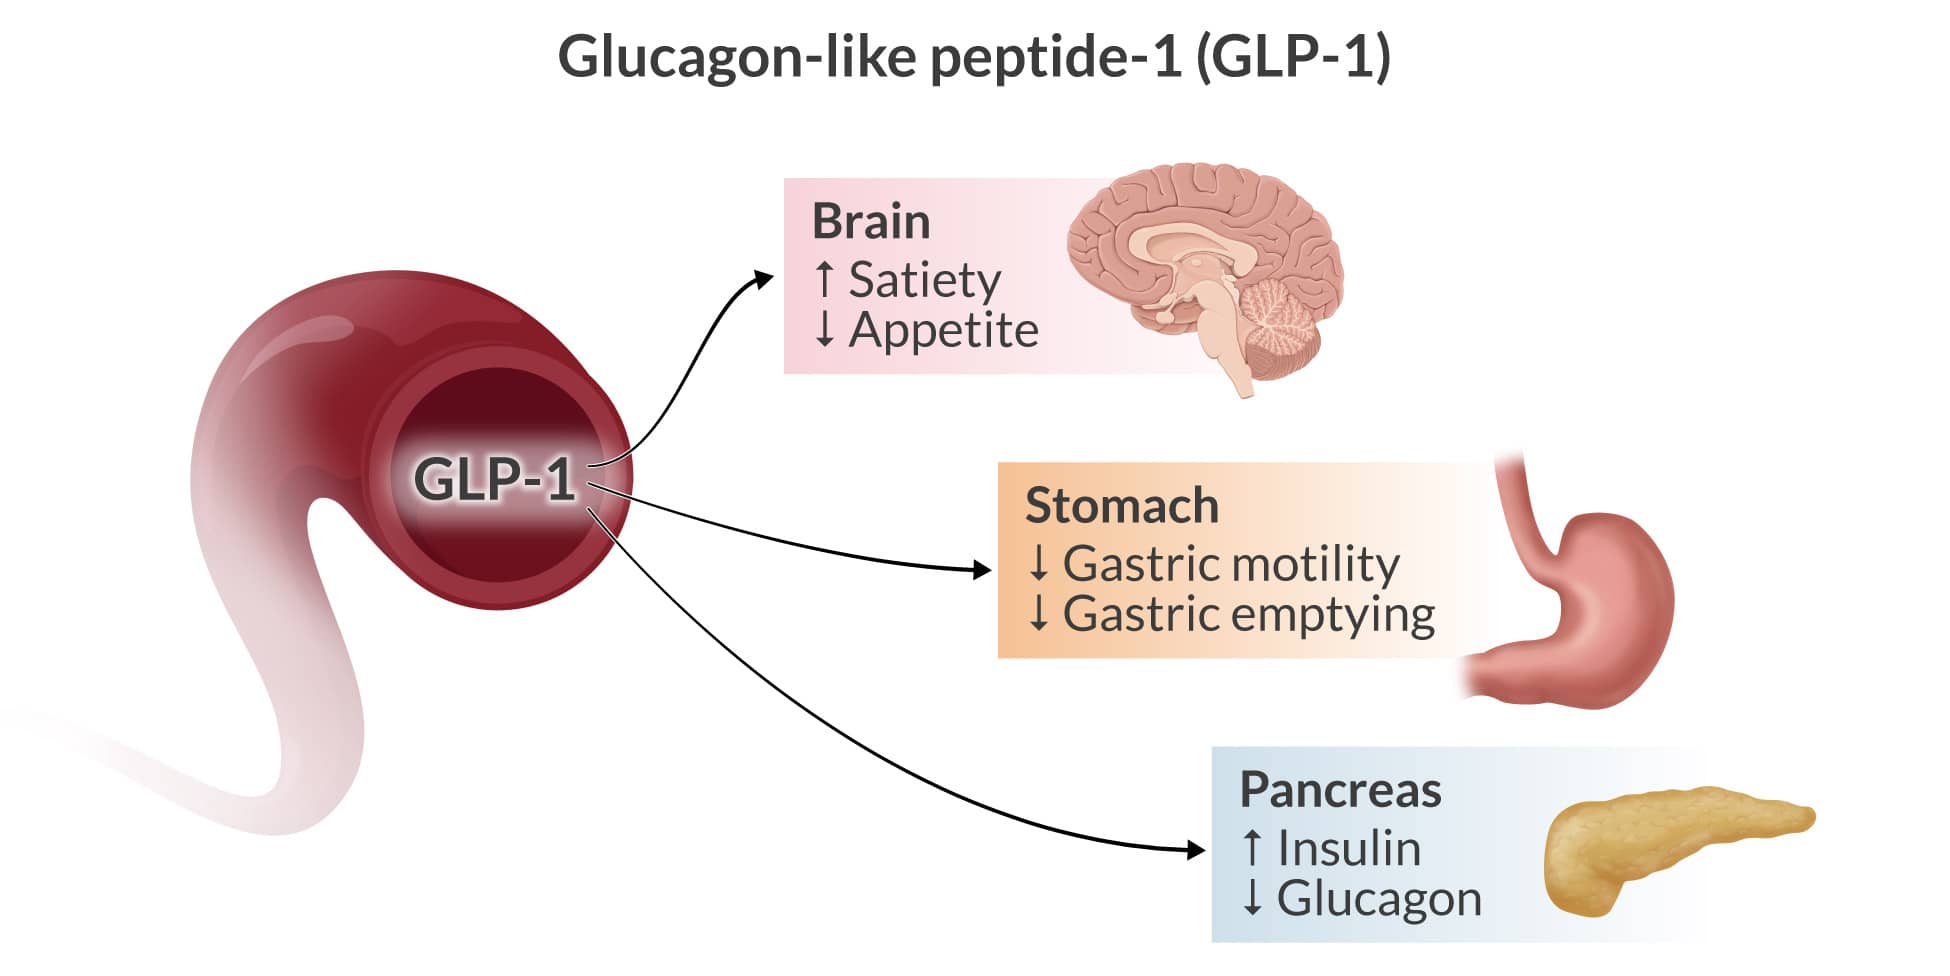
- Weight loss is officially recognized as a therapeutic goal. The recommendations acknowledge that a 5–10 % reduction in body weight can improve glycaemic control, so weight outcomes are now listed alongside HbA1c targets.
- Combination therapy flexibility. The guidelines allow GLP‑1 agonists to be paired with SGLT‑2 inhibitors or basal insulin earlier than before, provided safety checks are observed.
How the Guidelines Influence Treatment Choices
For a patient newly diagnosed with type 2 diabetes, the decision tree now starts with a cardiovascular risk assessment. If the individual has established CVD, chronic kidney disease, or multiple risk factors, a GLP‑1 agent with proven MACE reduction—such as semaglutide or liraglutide—is recommended as a first‑line injectable.
Conversely, patients without evident cardiovascular disease but with significant obesity may receive a GLP‑1 therapy chosen for its weight‑loss potency. The guidelines specifically note that agents offering greater than 5 % average weight loss are preferred in this subgroup.
Another shift is the timing of insulin introduction. Historically, basal insulin was added after oral agents failed. The updated guidance suggests that a GLP‑1 agonist can be introduced concurrently with basal insulin when rapid glycaemic control is needed, reducing the total insulin dose and potentially lowering hypoglycaemia risk.
Practical Steps for Clinicians and Patients
Implementing the new recommendations doesn’t require a complete overhaul of practice; a few focused actions can bridge the gap.
- Screen for cardiovascular risk. Use a simple checklist—history of myocardial infarction, stroke, peripheral artery disease, or a calculated ASCVD risk score—to decide whether a cardio‑protective GLP‑1 is warranted.
- Discuss weight goals early. Ask patients about their weight‑management priorities. If losing 5–10 % of body weight is meaningful, choose an agent with robust weight‑loss data.
- Review renal function. While most GLP‑1 agents are safe down to an eGFR of 30 mL/min/1.73 m², some require dose adjustments. Confirm the latest label information before prescribing.
- Consider combination therapy. For patients already on SGLT‑2 inhibitors, adding a GLP‑1 can amplify both glucose‑lowering and cardioprotective effects. Coordinate dosing schedules to minimise gastrointestinal side‑effects.
- Educate on injection technique. Simple demonstrations and written guides reduce anxiety and improve adherence, especially for those new to injectable therapies.
Common Misunderstandings About GLP‑1 Therapy
Even seasoned practitioners sometimes carry outdated notions. Let’s set the record straight.
- “GLP‑1 agents cause severe nausea for everyone.” In reality, gastrointestinal side‑effects are dose‑dependent and often diminish after the titration phase. Starting at a low dose and slowly increasing can mitigate discomfort for most patients.
- “Only overweight patients benefit.” While weight loss is a prominent advantage, GLP‑1 drugs also improve beta‑cell function and reduce blood pressure, offering benefits beyond the scale.
- “These drugs are too expensive for routine use.” Insurance coverage has expanded dramatically since the cardiovascular outcome trials, and many plans now list GLP‑1 agents alongside metformin and SGLT‑2 inhibitors.
- “Insulin must come before GLP‑1.” The guidelines now allow a GLP‑1 to be introduced alongside basal insulin, especially when rapid HbA1c reduction is needed.
Frequently Asked Questions
What makes the new IGLP‑1 guidelines different from older versions? The latest edition emphasizes cardiovascular risk, integrates weight loss as a therapeutic target, and offers greater flexibility for combination therapy, reflecting data from recent outcome trials.
Can I use a GLP‑1 agonist if I have mild kidney disease? Most GLP‑1 agents are safe down to an eGFR of 30 mL/min/1.73 m², but you should confirm the specific product’s labeling and monitor renal function regularly.
Do I need to stay on GLP‑1 therapy for life? Not necessarily. If glycaemic control is achieved and weight goals are met, clinicians may consider tapering, but any changes should be made gradually and under medical supervision.
How quickly can I expect to see weight loss? Many patients notice modest reductions within the first 8–12 weeks, with more pronounced results emerging after six months of consistent therapy.